



Knee Red Flags and Knee Replacement: When to Worry, and When Surgery Makes Sense
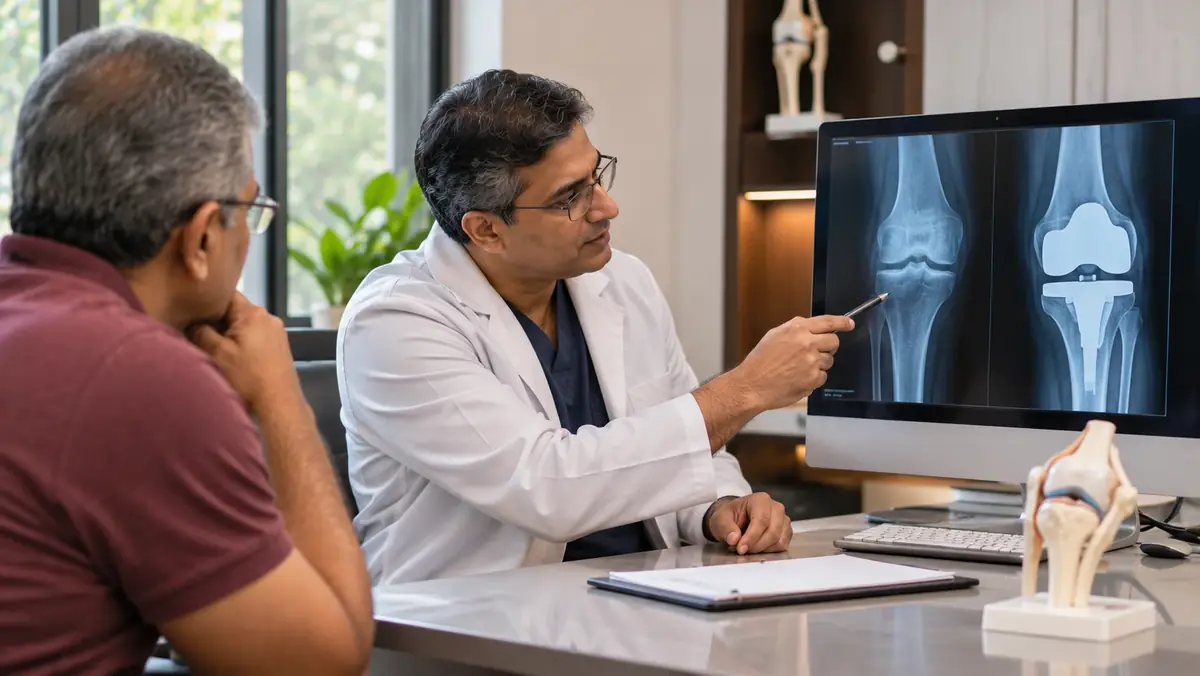
People are often surprised when an orthopaedic surgeon tells them they don’t need surgery. They’re even more surprised when I tell them it’s one of my favourite things to say.
Most knee pain can be managed with exercise, weight control and good self-care. But some symptoms should never be ignored. And for a smaller group of people, surgery does eventually become the right choice, and delaying it only means more years of pain. My job is to tell those two groups apart, honestly. This article will help you do some of that thinking yourself.
Red flags: get medical help promptly
Get urgent or same-day medical attention if you have:
- A hot, red, very swollen knee, especially with fever or feeling unwell. This can be an infection in the joint and needs urgent treatment.
- Inability to put weight on the leg or move the knee after a fall or twisting injury.
- Visible deformity or severe pain after an injury.
- A knee that locks (can’t fully straighten) or repeatedly gives way.
- Pain, swelling or warmth in the calf (a possible blood clot), or sudden breathlessness with leg pain.
- Numbness, weakness or loss of control in the leg.
- Constant pain at night that rest doesn’t ease, or knee pain with unexplained weight loss.
None of these is typical of straightforward osteoarthritis, and no online article, including this one, replaces an examination. If any of these apply to you, please stop reading and get seen.
See a doctor soon (within days to weeks) if
- Your knee pain has lasted more than a few weeks.
- Swelling keeps coming back.
- Pain is limiting walking, stairs or sleep.
- You’re relying on painkillers most days.
- The shape of your knee is changing.
What to try before surgery
The 2019 ACR/Arthritis Foundation guideline strongly recommends exercise, weight loss where appropriate, self-management programmes, tai chi, a cane, bracing for certain types of knee OA, anti-inflammatory medicines (gels and tablets) and steroid injections as part of a complete plan [1]. A Cochrane review found that the benefit of exercise lasts at least two to six months after supervised treatment ends [2].
A proper trial of non-surgical care means doing these consistently, ideally with professional guidance, for at least a few months. When a patient tells me “physio didn’t work”, my next question is always: what exactly did you do, and for how long? Often the honest answer is a handful of sessions and an exercise sheet that went into a drawer. That isn’t a failed treatment. It’s a treatment that never really started.
When I consider a knee replacement
I start discussing total knee replacement when:
- Pain and stiffness are severe and persist despite consistent non-surgical treatment.
- Everyday activities like walking, sleeping, dressing or using stairs are seriously limited.
- X-rays show advanced joint damage.
- You’re medically fit for surgery and willing to commit to rehabilitation afterwards.
All four matter. An advanced X-ray on its own is not a reason to operate. And being willing to do the rehab is not a formality. The operation is only part of the result. The rest happens in the weeks of physiotherapy that follow.
In India, knee OA is common and the demand for knee replacement is significant. The Government of India’s Department of Health Research commissioned a national health technology assessment on total knee replacement for knee OA in 2023, which shows how large the issue has become [3].
Preparing well, whether or not you need surgery
People who go into surgery with stronger muscles, a healthier weight and a clear understanding of recovery tend to be better placed. The good news is that the same steps that can postpone surgery, exercise and weight control, also prepare you for it if you do need it. That effort is never wasted.
Questions to ask your orthopaedic surgeon (including me)
- Have I tried enough non-surgical treatment, and is there anything else I should try first?
- What improvement in pain and function can I realistically expect?
- What are the risks in my particular case?
- What does rehabilitation involve, and how long will it take?
- Is a partial or total replacement more suitable for me?
A good surgeon will welcome these questions. If you feel rushed or pressured, get a second opinion.
Quick answers
At what age should I consider a knee replacement? There’s no single right age. The decision depends on your pain, function, X-ray findings and overall health, not age alone.
Can physiotherapy help before and after surgery? Yes. Prehabilitation before surgery and structured rehabilitation afterwards are key to recovery. Both online and in-person physiotherapy can play a role.
References
- Kolasinski SL, et al. 2019 ACR/Arthritis Foundation guideline for the management of osteoarthritis of the hand, hip, and knee. Arthritis Rheumatol. 2020;72(2):220–233.
- Fransen M, McConnell S, Harmer AR, et al. Exercise for osteoarthritis of the knee: a Cochrane systematic review. Br J Sports Med. 2015;49(24):1554–1557.
- Department of Health Research, Government of India. Health Technology Assessment of Total Knee Replacement in Patients with Osteoarthritis Knee in India. August 2023.
This article is for general education and does not replace advice from a qualified doctor. If you think you have a medical emergency, seek care immediately.